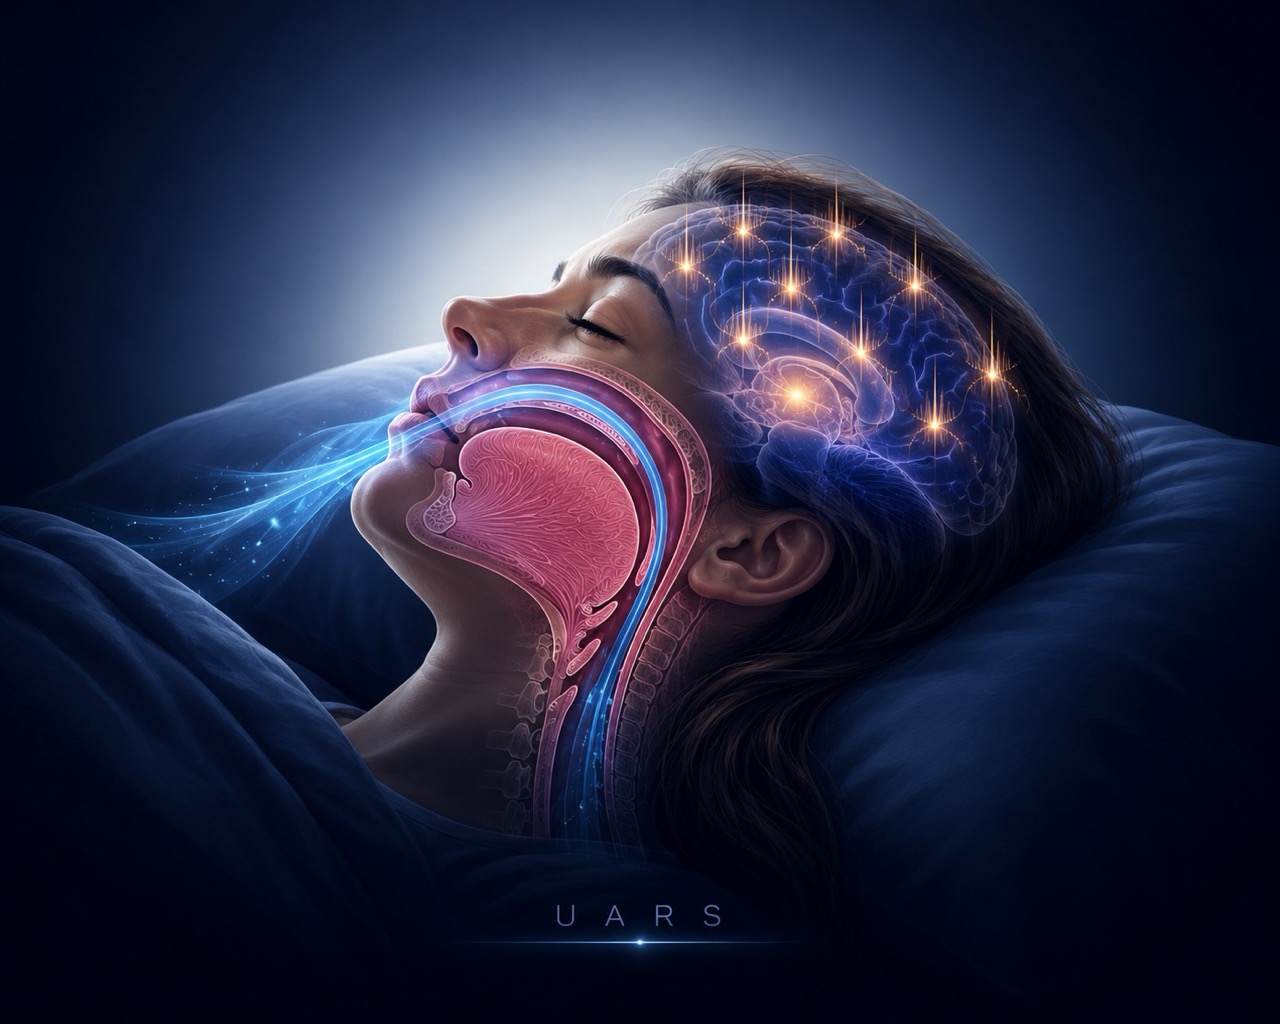
Upper Airway Resistance Syndrome (UARS): when your sleep study looks normal but you still feel exhausted
Many people undergo sleep testing because they experience persistent fatigue, daytime sleepiness, brain fog, poor concentration, or non-restorative sleep.
Sometimes the results are surprising.
Their sleep study may show:
- A normal Apnea-Hypopnea Index (AHI)
- Minimal oxygen desaturation
- No significant obstructive sleep apnea
Yet they continue to feel profoundly tired.
For years, these patients were often told that their sleep was normal.
Today, sleep specialists recognize that some individuals suffer from a related condition known as Upper Airway Resistance Syndrome (UARS).
Although UARS shares many features with obstructive sleep apnea (OSA), it often occurs without the dramatic breathing pauses or oxygen drops typically associated with sleep apnea.
Instead, the primary problem is repeated airway narrowing that forces the body to work harder to breathe, fragmenting sleep throughout the night.
What is UARS?
Upper Airway Resistance Syndrome is a form of sleep-disordered breathing characterized by:
- Increased resistance in the upper airway
- Increased respiratory effort
- Frequent sleep disruptions
- Minimal or absent oxygen desaturation
Unlike classic obstructive sleep apnea, the airway usually does not collapse completely.
Instead, the airway narrows just enough to make breathing more difficult.
The brain responds by briefly arousing from sleep to restore normal airflow.
Most patients never remember these awakenings.
However, they may occur dozens or even hundreds of times per night.
UARS versus obstructive sleep apnea
UARS and OSA exist along the same spectrum of upper airway dysfunction.
The difference lies in severity.
Obstructive Sleep Apnea
- Complete or near-complete airway collapse
- Apneas and hypopneas
- Frequent oxygen desaturation
- Elevated AHI
UARS
- Partial airway narrowing
- Increased airway resistance
- Frequent respiratory effort-related arousals (RERAs)
- Often normal oxygen saturation
- Low or normal AHI
In many cases, UARS may represent an earlier or milder manifestation of airway instability.
What happens during the night?
As sleep deepens, muscles supporting the airway relax.
In patients with UARS:
- The airway becomes narrower
- Airflow becomes restricted
- Breathing effort increases
The body compensates by working harder to inhale.
Eventually, the brain detects this increased effort and briefly arouses from sleep.
This sequence typically follows:
- Airway narrows
- Flow limitation develops
- Respiratory effort increases
- Brief arousal occurs
- Airway reopens
The cycle then repeats.
Night after night.
Why oxygen levels often remain normal
One reason UARS is frequently overlooked is that oxygen saturation often remains relatively stable.
Most people associate sleep-disordered breathing with oxygen drops.
However, oxygen deprivation is not the only mechanism that disrupts sleep.
Repeated arousals alone can significantly impair sleep quality.
Patients may therefore experience severe symptoms despite:
- Normal oxygen saturation
- Normal ODI
- Mild or normal AHI
This explains why many individuals feel worse than their sleep study numbers suggest.
The role of flow limitation
Flow limitation is one of the hallmarks of UARS.
Rather than complete airway collapse, airflow becomes progressively restricted.
The airway remains open, but breathing becomes inefficient.
Modern sleep laboratories often identify flow limitation by observing:
- Flattened inspiratory airflow
- Increased respiratory effort
- Repeated respiratory arousals
Many advanced PAP devices can also detect flow limitation patterns.
Respiratory effort-related arousals (RERAs)
RERAs are central to understanding UARS.
A respiratory effort-related arousal occurs when:
- Breathing becomes increasingly difficult
- Respiratory effort rises
- The brain briefly awakens
without meeting formal criteria for apnea or hypopnea.
Although these arousals may last only a few seconds, they interrupt normal sleep architecture.
Over time, hundreds of RERAs can produce profound fatigue.
Common symptoms of UARS
Patients with UARS frequently report:
- Chronic fatigue
- Excessive daytime sleepiness
- Brain fog
- Difficulty concentrating
- Memory problems
- Frequent awakenings
- Morning headaches
- Non-restorative sleep
- Anxiety-like symptoms
- Unrefreshing sleep despite adequate sleep duration
Many describe feeling exhausted even after spending eight or more hours in bed.
Who develops UARS?
Unlike traditional obstructive sleep apnea, UARS is often observed in:
- Younger adults
- Women
- Individuals with normal body weight
- Patients without obvious snoring
- Patients with subtle craniofacial airway narrowing
Because these individuals do not fit the classic sleep apnea profile, diagnosis may be delayed.
Why UARS is often missed
Several factors contribute to underdiagnosis.
Reliance on AHI
Many sleep studies focus heavily on apnea and hypopnea counts.
If AHI is normal, clinically important breathing disturbances may be overlooked.
Home sleep tests
Many home sleep apnea tests cannot reliably identify:
- RERAs
- Flow limitation
- Sleep-stage arousals
As a result, UARS may be missed entirely.
Normal oxygen saturation
Stable oxygen levels can create the false impression that sleep quality is unaffected.
How UARS is diagnosed
Diagnosis generally requires comprehensive sleep evaluation.
Polysomnography may reveal:
- Frequent RERAs
- Elevated Respiratory Disturbance Index (RDI)
- Flow limitation
- Increased respiratory effort
- Sleep fragmentation
The combination of symptoms and physiological findings is often more important than AHI alone.
Treatment options
Treatment focuses on improving airway stability and reducing respiratory effort.
Potential approaches include:
Positive airway pressure (PAP)
CPAP or APAP therapy may reduce:
- Flow limitation
- RERAs
- Sleep fragmentation
Oral appliance therapy
Mandibular advancement devices may help maintain airway patency.
Positional therapy
Some patients experience improvement by avoiding supine sleep.
Addressing nasal obstruction
Nasal resistance can worsen airflow limitation and may require treatment.
Is UARS a separate disorder?
This remains an area of ongoing debate.
Some experts view UARS as:
- A distinct disorder
Others view it as:
- A phenotype within the broader spectrum of obstructive sleep-disordered breathing
Regardless of classification, the symptoms and physiological consequences are very real.
Why UARS matters
For many patients, UARS explains a frustrating disconnect:
- Severe symptoms
- Apparently normal sleep studies
Recognition of UARS highlights an important principle in sleep medicine:
Sleep quality is not determined solely by oxygen levels or apnea counts.
Repeated airway resistance and sleep fragmentation can profoundly affect health, cognition, and quality of life even when traditional sleep apnea metrics appear reassuring.
Key takeaways
- UARS is a form of sleep-disordered breathing characterized by increased airway resistance rather than complete airway collapse.
- Patients often have normal oxygen saturation and low AHI.
- Flow limitation and RERAs are key physiological features.
- Repeated sleep fragmentation can cause severe fatigue despite normal sleep apnea scores.
- UARS is frequently underdiagnosed, particularly in younger and non-obese individuals.
- Comprehensive sleep evaluation is often necessary for accurate diagnosis.
References
- Guilleminault C. Upper Airway Resistance Syndrome.
- American Academy of Sleep Medicine (AASM) Manual for the Scoring of Sleep and Associated Events.
- Malhotra A, Ayappa I, Ayas N, et al. Metrics of Sleep Apnea Severity Beyond the Apnea-Hypopnea Index.
- Eckert DJ. Pathophysiology and Phenotypes of Obstructive Sleep Apnea.